Anesthesia

Intubation Contraindications

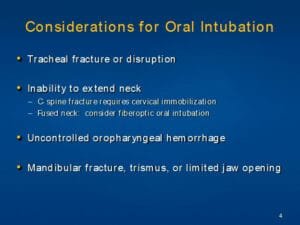
Intubation contraindications can be divided into those Both Nasal and Oral lntubation and those for Nasal Intubation. Both Nasal and Oral lntubation Contraindications • Laryngeal edema. • Epiglottitis. • Laryngotracheobronchitis This is one among the important Intubation Contraindications. In these conditions the airway is already compromised giving very little place for the endotracheal Tube to

Intubation Contraindications Read More »

Awake Craniotomy Anesthesia

The anesthesiologist should know that the essential element of an “anesthetic” for an Awake Craniotomy Anesthesia is the surgeon’s local anesthetic technique. Craniotomy is required for removal of space occupying lesions, intracranial vascular pathologies and for drainage of extradural or intradural haematoma. Most important postoperative considerations are regulation of patient’s ICP status, maintenance of cerebral

Awake Craniotomy Anesthesia Read More »

Anesthesia in Neurological Disease

Patients with primary neurodegenerative undergoing Anesthesia in Neurological Disease  (Parkinson’s disease, Huntington’s chorea, Alzheimer’s, amyotrophic lateral sclerosis ) or demyelinating diseases (Guillain-Barre’ syndrome, multiple sclerosis, myeloneuropathies) suffer from progressive and sometimes incurable neurologic impairment, neuromuscular involvement, dysautonomia and pulmonary insufficiency. Elective surgery should be scheduled to coincide with periods of remission along with right application

Anesthesia in Neurological Disease Read More »

Methoxyflurane Anesthesia

Methoxyflurane Anesthesia is a halogenated hydrocarbon now obsolete. Physical properties: Colorless, fruity liquid, non-flammable, boiling point of 104°C, blood/gas coefficient 13, oil /gas 825, VP 25 mm Hg, MAC 0.2%, metabolism 50-75%. Methoxyflurane Anesthesia is metabolized to dichloroacetic acid and methoxydifluoro acetic acid and fluoride in high amount which proved nephrotoxic; due to this it

Methoxyflurane Anesthesia Read More »

Anatomical dead space and its Anesthetic implications

Total dead space (Physiological dead space) = Anatomical dead space + Alveolar dead space. Anatomical Dead Space It is constituted by air which is not participating in diffusion. Therefore it is constituted by air present in nose, trachea and bronchial tree (up to terminal bronchioles). Normally it is 30% of tidal volume or 2 ml/kg or 150 ml. Anatomical dead

Anatomical dead space and its Anesthetic implications Read More »

Charle’s law

Charle’s Law: A Fundamental Gas Law What is Charle’s Law? Charle’s Law is a fundamental principle in thermodynamics that describes how gases behave under varying conditions of temperature and volume. Formulated by Jacques Charles in the late 18th century, this law states that the volume of a gas is directly proportional to its absolute temperature,

Charle’s law Read More »

Scroll to Top