Anesthesia

Anatomical dead space and its Anesthetic implications

Total dead space (Physiological dead space) = Anatomical dead space + Alveolar dead space. Anatomical Dead Space It is constituted by air which is not participating in diffusion. Therefore it is constituted by air present in nose, trachea and bronchial tree (up to terminal bronchioles). Normally it is 30% of tidal volume or 2 ml/kg or 150 ml. Anatomical dead […]

Anatomical dead space and its Anesthetic implications Read More »
CEA Anesthesia

CEA Anesthesia or Carotid endarterectomy anesthesia can be general or regional or combined. Here is a discussion on the relative advantages and disadvantageous of the different types. Mc CaI Thyet al conducted a prospective, randomized trial investigating patient experience of CEA Anesthesia under local or general anesthesia in 176 patients and found that the recovery

CEA Anesthesia Read More »

Anesthesia for Carotid Endarterectomy

Anesthesia for Carotid Endarterectomy is of proven benefit to reduce the risk of stroke in patients with high-grade stenosis of the internal carotid artery. Since the disease is atherosclerotic in origin, these patients often are prone to a variety of cerebrovascular and myocardial complications during the perioperative phase. Anesthesia for Carotid Endarterectomy demands excellent haemodynamic

Anesthesia for Carotid Endarterectomy Read More »

Intubation Complications

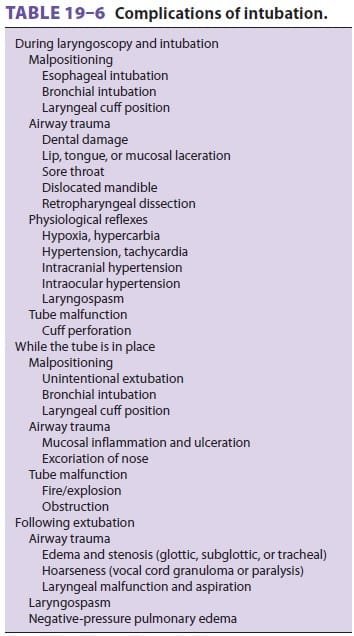
Endotracheal intubation complications can be intraoperative, postoperative or delayed. The following are the immediate intubation complications that are commonly seen: Esophageal intubation: This is a hazardous complication. Can be done as a mistake. If not detected in time can cause severe hypoxia and even death. This can be easily be detected by measuring carbon dioxide

Intubation Complications Read More »

Scroll to Top